

Aesthetics · Comparison
Veneers or composite bonding: which makes sense when
Both treatments are offered for the same complaints, yet they differ in reversibility, longevity and cost. This article compares them across six criteria instead of declaring one the winner.

The short answer
Ceramic veneers are laboratory-made, usually require enamel removal, and showed 96.8% survival at a mean 10.4 years in a meta-analysis of 29 clinical studies. Composite bonding is sculpted directly in one visit and removes little or no tooth structure, but a review of 1,821 anterior composite restorations followed at least three years reported an overall failure rate of 24.1%.
Key points
- Composite bonding is built directly in the mouth in a single visit; a ceramic veneer is laboratory-made and bonded at a separate appointment.
- A meta-analysis of 29 clinical studies reported 96.8% survival for lithium disilicate veneers at a mean follow-up of 10.4 years.
- A review of 17 studies covering 1,821 anterior composite restorations followed at least three years reported an overall failure rate of 24.1% and annual failure of 0 to 4.1%.
- Composite picks up stain over time and needs periodic polishing; ceramic is colour-stable.
- Bonding can usually be repaired in the mouth, whereas a fractured ceramic veneer is replaced.
Veneers and bonding: the real difference
The difference is not cheap versus expensive, it is how each is made. Composite bonding is a resin applied in layers and shaped directly on the tooth while you are in the chair. You see the result in the same visit.
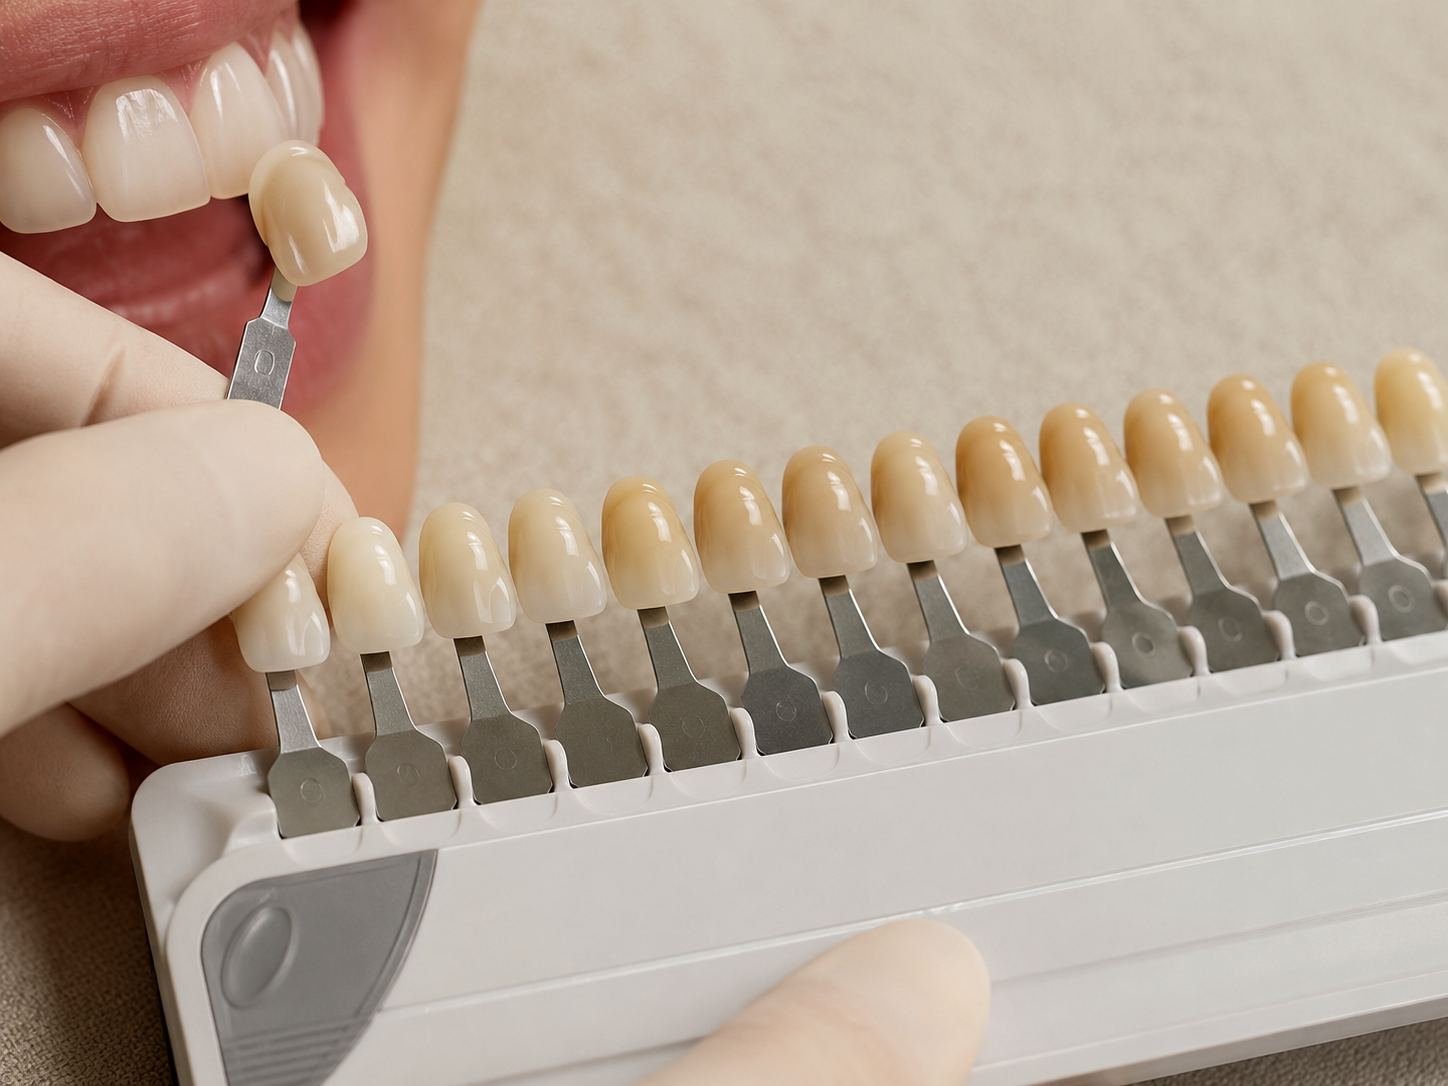
A ceramic veneer is designed, made in a laboratory and bonded afterwards. Temporary veneers are worn in between. Ceramic is harder, more colour-stable and more wear-resistant than composite, but making room for it usually means removing enamel.
Every other difference follows from that: reversibility, longevity, how the colour behaves, whether it can be repaired, how many visits are needed and how the cost is built.
Reversibility and tooth structure
Bonding often removes no tooth structure at all, or very little. If the composite is taken off, the tooth is largely as it was. That makes it a sensible option for younger patients and when the decision about a final appearance has not settled yet.
Veneers in most cases involve removing a thin layer of enamel. That layer does not grow back and the tooth stays covered from then on. Minimal-preparation and no-preparation cases exist, typically small, worn or inward-standing teeth, but they are identified after examination and a diagnostic model rather than on request.
This is the difference we discuss first. Most other factors can be revisited later. Removed tooth structure cannot.
Longevity: what the data show
A systematic review and meta-analysis of 29 clinical studies reported 96.8% survival for lithium disilicate veneers at a mean follow-up of 10.4 years. A separate retrospective study of 318 veneers found 94.4% survival at five years, 93.5% at ten and 82.9% at twenty, with failure risk 7.7 times higher in patients with bruxism.
For composite, a review of 17 studies covering 1,821 anterior restorations followed at least three years reported an overall failure rate of 24.1% and annual failure of 0 to 4.1%. In posterior teeth, 90% of studies with at least five years of follow-up reported annual failure rates of 1 to 3%.
These datasets are not directly comparable, since the teeth, indications and failure criteria differ. The practical conclusion holds nonetheless: ceramic lasts longer, composite needs servicing more often.
Colour and staining
Composite is porous at a microscopic scale. Over the years the surface takes up pigment from coffee, tea, red wine and tobacco, and margins can darken. Some of that is removed by polishing at routine hygiene visits.
Ceramic is colour-stable. When its appearance changes, the cause is usually external: plaque accumulating at the gum margin, or the neighbouring natural teeth darkening. For that reason, if whitening is part of the plan, it is completed before the ceramic is made, not after.
Repair, replacement and cost over time
Bonding is repairable. A chipped corner or a worn edge can often be added to in the mouth without removing the whole restoration. That is a genuine advantage and one reason the treatment costs less at the outset.
A ceramic veneer is generally not repaired. A fracture through the full thickness means a new veneer. Comparing prices therefore only makes sense over a period: the lower initial cost of bonding includes more servicing, and the higher initial cost of ceramic buys a longer interval without intervention.
Neither veneers nor bonding have a published price, because the number of teeth and the scope of work differ in each case. The quotation is issued in writing after examination. Our published costs for other treatments are on the price list.
How the choice is made in practice
Bonding is sensible when the change is small, the teeth are sound, you want a reversible option, or you want to see the effect before committing to something irreversible. It also works well as a first stage for younger patients.
Veneers make sense when the colour does not respond to whitening, when the change in shape is larger, when extensive old restorations are already present, or when you want a longer horizon and accept the preparation involved.
With bruxism or an unstable bite, the cause comes first, whether that is a night guard or correcting the alignment, and only then the material. That applies equally to both treatments.
| Criterion | Ceramic veneers | Composite bonding |
|---|---|---|
| Reversibility | Usually irreversible, a layer of enamel is removed | Often reversible, little or no tooth structure removed |
| Longevity | 96.8% survival at a mean 10.4 years (meta-analysis of 29 studies) | 24.1% overall failure across 1,821 anterior restorations followed 3 years or more |
| Staining | Ceramic is colour-stable | Picks up stain over time, needs periodic polishing |
| Cost basis | Clinical work plus laboratory fabrication per tooth, quoted in writing after examination | Clinical work per tooth, no laboratory stage, quoted in writing after examination |
| Repairability | Normally replaced rather than repaired | Normally repaired directly in the mouth |
| Number of visits | Typically two or more, with temporaries in between | Typically one visit |
The Club awaits you
You receive a written plan for both approaches, with items and timelines. Call +359 896 121 314 or visit us at 28 Dr Lyuben Popov Street, Briz, Varna.
What the evidence shows
96.8%
survival of lithium disilicate veneers at a mean 10.4 years
Systematic review and meta-analysis of 29 clinical studies (2025): 96.8% for lithium disilicate, 96.1% for feldspathic ceramic, 93.7% for leucite-reinforced glass ceramic, with no statistically significant difference between materials. In a retrospective study of 318 veneers, failure risk was 7.7 times higher in patients with bruxism.
Frequently asked questions
Frequently asked questions
Yes, and it is a common sequence. Bonding lets you test shape and length with little or no tooth structure removed. If you decide years later to move to ceramic, the starting position is still good. The reverse route, from veneers back to bonding, is not equivalent, because the enamel has already gone.
Both can look natural. The difference is how they behave over time. Freshly placed composite often looks excellent, but its surface changes. Ceramic keeps its translucency and gloss for longer. With equally skilled work, ceramic holds the result longer and composite needs more maintenance to keep it.
Bonding, in most cases. It is often placed with no reduction at all or with minimal surface conditioning. Veneers need space for the ceramic. The exception is small or worn teeth, where a veneer can sometimes be bonded with very little preparation, which is assessed after examination and a model.
There is no fixed interval. Studies report annual failure rates of 0 to 4.1% for anterior composite restorations, meaning some need attention each year while others last a long time. Polishing at hygiene visits and controlling night-time grinding both extend the working life.
Through an examination, photographs and a conversation about what you expect. The first step with us is an online case review from your CBCT or X-ray, including online. We show both options against the planned outcome, and for larger changes we make a mock-up so you can judge the result before any tooth structure is removed.
Related treatments

Clear aligners or fixed braces: what the evidence shows
The two approaches do not cover the same range of cases. This article reports the evidence in both directions: where aligners win, and where they remain weaker than fixed appliances.
Read moreHow long composite bonding lasts and what shortens its life
Composite bonding has no single expiry date. It lasts differently in different mouths and on different teeth. Here is what the studies report and which factors matter most.
Read moreClosing a gap between the front teeth with composite bonding
A gap between the front teeth can be closed in one visit with composite, or closed by moving the teeth themselves. The two routes give a different result and a different lifespan.
Read more